

Buckle up, buttercup. I’m still over here in…
No Isolation Land: The Sex Virus Years.
Today’s dive began by asking “is herpes very contagious?” in the google search bar. I think you and I both know what the search turned up.
As you may already know, I’ve written at length about several of these purported sex viruses. See HIV + HPV here, herpes here, and general problems with The Science™ here, here, and here.
I just wanted to clarify that the current vibe is still the same as what I learned from all the fear porn every STD poster ever. Which is that even though herpes plays hide and seek once it’s inside the body…it’s definitely not a hider when it’s out in the wild and leaping off lips and booties.
Let’s review how contagious herpes is. Spoiler alert…
SO CONTAGIOUS 😲
(👆 I wish I could make that bigger and in bubble letters.)
I might’ve broken the internet for a sec when I dared to ask that question.
✋In fact, it’s probably best not say herpes out loud while you’re reading this because you might catch it from saying the word.
The first website in my search results checks all the usual boxes:
Digital art of the never isolated virus 👇

👆Look at that metallic sheen!! It’s like it’s already stabbing you in your private bits 🦠. Or your mouth🦠. Or eyes🦠. Or brain🦠. Actually it can stab you anywhere🧟♂️. Soooooo many people have it. Like almost more than 100%.
They might not know it, even though they are spreading it.
✋Or they might have terrible symptoms.
It’s spread through contact with open sores.
✋Or not…when it’s just spread through regular skin.
HSV-1 makes sores in the mouth.
✋Except sometimes when it makes sores on the genitals.
HSV-2 makes sores on the genitals.
✋Except sometimes when it makes sores in the mouth.
✋Actually, sores can happen anywhere🤚
Just like green eggs and ham.

The only way to really know if you have it is by doing (drum roll please)…A TEST!!! Because no symptoms and stuff.
This virus likes to play hide and seek by “hiding in the nerves” (← their words, not mine, btw, see below).

From The Well Project:
Herpes is a sexually transmitted infection (STI) caused by a virus that lives in the nerves. There are two common types of herpes:
Herpes simplex type 1 (HSV-1) usually causes cold sores around the mouth
Herpes simplex type 2 (HSV-2) usually causes sores in the genital area
However, it is possible to get HSV-2 in the mouth and HSV-1 in the genital area.
HSV is different from varicella-zoster, the virus that causes shingles (also called herpes zoster) as well as chickenpox, although the two viruses are in the same family. For more information, please see our fact sheet Shingles and HIV.
People with herpes may have no symptoms. If they do have symptoms, these are usually itchy or painful blisters. The virus is spread through skin-to-skin contact with sores, but it may also spread through the normal unbroken skin of a person who has herpes. Many people who have never had symptoms may not realize that they have herpes. Currently there are no recommended tests to look for this infection other than a physical exam and culture of a blister. There are blood tests that look for certain antibodies in your body to determine whether or not you have ever been exposed to HSV-1 or HSV-2. In most people, the sores come and go, but the virus stays in the body for life. Sometimes there are no symptoms because the virus is "hiding" in the nerves.
For the record…
Of the more than 100 known types of the herpes virus, only eight affect humans. Two of these are herpes simplex viruses (HSV-1 and -2), which can cause genital herpes, and the other six are human herpesviruses (HHV) types 3 through 8, which can cause skin, immune, and other issues.
Here are the Medical Derm Specialists weighing in:
📣 SO CONTAGIOUS 😲

In my last post I looked into one paper that was being swung around like a giant, iron clad proof ax. As usual, I found plenty of monkey kidney cells and fetal calf serum.
But you know I just couldn’t stop there and I had to check up on the original “isolation” of this big bad herpetic beast virus. Whilst I was on this mission, digging through Dulbecco’s Eagle Medium, fresh egg yolk, normal calf serum, and Secondary Rabbit Kidney Cells…
Buffered saline (BS) means 0.01 Al phosphate-buffered saline at pH 7.2 free of potassium, and PBS refers to Dulbecco and Vogt's phosphate-buffered saline free of divalent cations (6). BS containing fresh egg-yolk at 0.1 % (yolk-saline) was used as a virus diluent in infectivity titration. YLE and MEM media. Earle's balanced salt solution containing 0.5% lactalbumin hydrolysate and 0.1 % yeast extract (YLE) and Eagle's minimum essential medium (MEM) were adjusted to pH 7.2 with NaHCO3, and supplemented with 2 or 20% inactivated normal calf serum, being referred to as YLE2CS, YLE2OCS, MEM2CS or MEM2OCS depending on the base medium and calf serum concentration. All these media contained appropriate amounts of antibiotics.
Cell monolayers were prepared in rubber-stoppered glass culture bottles, 4 •~ 7 •~ 2.5 cm, dispensing 5 ml per bottle of a cell suspension, or in Leighton tubes dispensing 1 ml per tube of cells. Primary cynomolgus monkey kidney (MK) cells were kindly donated by Dr. M. Nakano, the National Institute of Health of Japan, Tokyo. Secondary rabbit kidney (SRK) cells were prepared in this laboratory from 4-week-old rabbits. HeLa S3 clone (13), L 929 (14), Vero (18) and RK-13 cells (1) had been maintained in our laboratory. The growth and maintenance media for these cells were MEM1OCS and MEM2CS, respectively, except for MK cells which were grown in LE (YLE minus yeast extract) medium supplemented with 2% calf serum and maintained after virus infection with serum-free LE medium. CE cells were processed according to a previous description (15).
I ran across this study:
Isolation and Localization of Herpes Simplex Virus Type 1
mRNA
👆And it does not disappoint in the fuckery department! By the way, I’m coming to learn that anytime DNA or RNA is involved, you get a whole other almost unreadable layer of fun that comes after the monkey kidney cells and fetal calf serum part.
And MY GOODNESS is there ever an abundance of studies looking at herpes mRNA…I’m not going to list them because it’s so much, but I will summarize the evolution of the bullshit.
Evolution of the Bullshit
Tangible Fuckery
This bullshit research started just like all of it does, with the foundational papers that added stuff to “isolate” ”the virus”, that they had already decided was there. I’m going to refer to this as Tangible Fuckery. The tangible fuckery involves cell culture plates that host a variety of cells which are almost never human. These cells + “the virus” are then fed a delectable diet, perhaps of serum, extracted from the fetus of a pregnant cow, and often other things like Dulbecco’s Eagle Medium, rabbit serum, or fresh egg yolks and yeast for a period of time before being starved and poisoned in various ways.
Herpes was a stubborn beast of a virus, and The Science™ needed new tools so they could predict what Herpes was thinking by reading its blueprint….
Enter Digital Fuckery
The Science™ then accelerated its speed to Digital Fuckery.

Digital Fuckery moved to RNA and transcription factors, latency-associated transcripts, and then latency-phase RNAs. Then came virion host shutoff (vhs/UL41) and mRNA decay followed by modern transcriptomics. These advances required big machines, computers, and plenty of smoke for the mirrors.

Now The Science™ could extract, convert, and decode, using Sequencing Sorcery. And with their algorithms and Molecular Karaoke Machines they knew that Herpes was not only a lover of fun games like hide and seek, but also liked to play Chucky.

Thanks to these awesome tools we know that Herpes, the Hide N Seek Chucky Virus, chops up little mRNAs with a RNA-cutting enzyme nano machete (known as UL41/vhs). This enzymatic thrash-cat supposedly destroys cellular mRNAs, conducts viral gene expression, and helps Herpes hide from the good guys (your immune system).

Hold that thought…
👉 I’m taking a detour👇
(Which will come as no shock to anyone who regularly reads this stack.)
Why? Because the tale of the systematic poisoning of the world continues to be a twisted one.
Ok…At the Chucky Chapter in my research, I happened to come across this note from leithian (who unfortunately doesn’t write a stack because I would totally read it):
Somehow I was unfamiliar with “Scoglio”. I also had not read (or even seen) this post by Unbekoming (I recommend reading in its entirety), or seen Tom Cowan’s interview with Scoglio (watch it):

We are going to get into some dense underbrush in the coming sections, so I’m not going to walk through the excellent work Unbekoming has already done. You can access the original Off Guardian interview with Stefano Scoglio here. For the purpose of this post, I will provide an overly simplified synopsis.
Stefano Scoglio was an Italian scientist and researcher who reviewed and analyzed the published covid literature in 2022. Scoglio logically dismantled the foundation of the mRNA vaccine platform, its lipid nano particle mRNA instruction delivery system, and subsequently all of the narratives around the infamous spike protein.
Scoglio points to Pfizer’s own Japanese biodistribution study which found that lipid nanoparticles were recovered unchanged from organs, proving they never entered cells to deliver their payload.
"If they had entered the cells, they would've been metabolized and you wouldn't have found them in the same way you have injected them," Scoglio explained.
What does this mean and why is it important? No cellular entry means no spike protein production, rendering the entire mechanistic explanation dubious, at best.
Scoglio goes on to outline how “testing” and “proving” antibody specificity to the spike protein uses extremely questionable methods involving always and only synthetic spike protein, “researchers are using non-existent entities to prove the existence of other non-existent entities”.
This fraudulent specificity has become so evident that, as Dr. Cowan noted in his discussion with Scoglio, the editor of a major neurology journal announced he would no longer accept papers based on antibody specificity, recognizing the entire premise as scientifically invalid.
I will address the antibody “testing” methodology in a bit. If you would like to delve deeper than what I am going to do, please see here.
Let’s circle back to where I was in my herpes research…Chapter Chucky: The mRNA Slasher Virus That Plays Hide N Seek in the Nerves.
Oh look, they’re making herpes mRNA vaccines with lipid nanoparticle delivery!👇
mRNA-1608 Herpes Vaccine Clinical Trials, Dosage, Indication, News, Side Effects
🤗 And I’ve got great news…Moderna is almost ready for Phase 3 Clinical Trials!
mRNA-1608 Herpes Vaccine Candidate Clinical Trials
As of 2025, Moderna publishes clinical trial updates at this web link. According to GlobalData, Phase II drugs for Genital Herpes have a 30% phase transition success rate, indicating a benchmark for progressing into Phase III.
A Phase 1/2, Randomized, Observer-Blind, Controlled, Dose-Ranging Study of mRNA-1608, an HSV-2 Therapeutic Candidate Vaccine, in Healthy Adults 18 to 55 Years of Age With Recurrent HSV-2 —Last updated September 24, 2024, has a completion date of 2025-04-11. This study aims to generate safety and immunogenicity data and establish a proof-of-concept of the clinical benefit of the mRNA-1608 vaccine candidate.
“This presents a fundamental paradox: if Scoglio is correct that nothing enters cells—as proven by the Japanese biodistribution study showing unchanged lipid nanoparticles in organs—then how could any technological payload, whether mRNA or undeclared elements, achieve its intended function?“
With purported herpes virus supposedly infecting nearly 100% of the population, we can only assume that this “vaccine” will follow a similar trajectory as HPV (don’t you want your daughter to be One Less???)…
Herpes mRNA Injection Clinical Trial Walk Through
This section is dense and I apologize. I’ve done my best to explain it simply, but like all The Science™, it is NEVER simple. The trial for this mRNA Herp jab is not yet published, so all we can look at is the design.
The following is directly from clinicaltrials.gov from Phase 1/2 trial for Moderna’s mRNA-1608 herpes injection. Phase 1 primarily focuses on “safety”, Phase 2 trials look at EFFICACY and dosage level. Let’s take a look at what’s available from the clinical trial for this injectable toxic bomb mRNA-1608.
We have some of the usual fuckery straight away. The “control” group is receiving BEXSERO. BEXSERO is a meningococcal injection, which to be clear, has many ingredients, and therefore is not inert.
Inert
a substance or treatment that has no active therapeutic effect
To be clearer…that means BEXSERO is CANNOT possibly be a true placebo control.

A true placebo control would be a group that received an inert treatment such as saline, designed to look like the treatment and be administered in exactly the same way. This ensures that only the specific effects of the active treatment can be measured.
For the record, a true placebo control does NOT look this👇
Participants with a history of recurrent genital herpes will be randomly assigned in a 1:1:1:1 ratio to receive mRNA-1608 at 1 of the 3 dose levels or control (BEXSERO) administered as 2 doses at 0 and 2 months (Day 1 and Day 57).
Biological: BEXSERO
A vaccine indicated for active immunization to prevent invasive disease caused by Neisseria meningitidis serogroup B.

Here is some information on common side effects following meningococcal injection:
DERMATOLOGIC
Very common (10% or more): Rash, redness/erythema
Common (1% to 10%): Eczema
Rare (0.01% to 0.1%): Urticaria
Rash was very commonly reported in patients 12 to 23 months of age but was reported as an uncommon side effect in this age group when they received a booster dose. Rash was commonly reported in patients 2 to 10 years of age.
To clarify my point here…
The injection that is being used as a placebo control comes with its own host of side effects (which include a variety of RASHES); of which up to HALF of all people will experience some form of.
This trial is determining whether this injection prevents a type of RASH.
Full disclosure…I did a brief search and did not see any glaring evidence that the meningococcal injections regularly trigger genital rashes that could be called herpes. HOWEVER after seeing researchers characterize Maddie de Garay’s symptoms (that resulted in hospitalization and an NG/feeding tube) as “a stomachache” during the covid clinical trials, I’m open to any rash being called herpes.

My point is that using a non-inert placebo creates opportunity for the fuckery we see time and time again during vaccine trials in two distinct ways.
If the “placebo” group experiences side effects similar to the treatment group it can make the treatment appear safer than it really is.
If the “control” triggers symptoms similar to those it is supposed to prevent, it will make the treatment look artificially effective.
Here’s how the injections will be administered in the mRNA-1608 trial:
Participants will receive 2 intramuscular (IM) injections of mRNA-1608 at Dose A, B, or C, each dose administered at 0 and 2 months (Day 1 and Day 57).
👉 Got that? This consists of two doses, that will be injected two months apart.
Now let’s look as some of the outcome measures.
Outcome Measures
Number of Genital Herpes Recurrences, Counted Starting 14 Days After the Second Study Injection to 6 Months After Second Study Injection [Time Frame: Day 71 to Day 225]
Number of Genital Herpes Recurrences, Counted Starting 14 Days After the Second Study Injection to 12 Months After Second Study Injection [Time Frame: Day 71 to Day 393]
Change From Baseline (28 Days Prior to the First Study Injection) to 2 Months After the Second Study Injection in Genital Herpes Lesion Rate (Proportion of Days With Lesions Present) [Time Frame: Baseline (Day -27 to Day 1), Day 85 to Day 113]
To calculate the 'Change from Baseline', the herpes lesion rate during the timeframe of Day 85 to Day 113 will be compared against the herpes lesion rate during the timeframe of Day -27 to Day 1 (Baseline).
Change From Baseline (28 Days Prior to the First Study Injection) to 6 Months After the Second Study Injection in Genital Herpes Lesion Rate (Proportion of Days With Lesions Present) [Time Frame: Baseline (Day -27 to Day 1), Day 197 to Day 225]
To calculate the 'Change from Baseline', the herpes lesion rate during the timeframe of Day 197 to Day 225 will be compared against the herpes lesion rate during the timeframe of Day -27 to Day 1 (Baseline).
Okie dokie…so we have some more typical fuckery here. Let’s go through it.
They start counting herpes recurrences beginning 14 DAYS AFTER THE SECOND INJECTION. This means 71 days after the first injection. So any qualifying rash occurring in the SEVENTY ONE DAYS AFTER A TOXIC EXPERIMENTAL BOMB IS INJECTED isn’t counted as an occurrence…or a failure of the treatment.
You might recall this strategy from the covid injection trials and subsequent post marketing data. Remember when people got ill any time between being injected with the first covid shot and two weeks after the second one… and were counted as unvaccinated? This is the same strategy.
Ok…back to more Outcome Measures Bullshit:
Change From Baseline (28 Days Prior to the First Study Injection) to 2 Months After the Second Study Injection in HSV-2 Genital Shedding Rate (Proportion of HSV-2 Deoxyribonucleic acid [DNA] Positive Anogenital Swabs) [Time Frame: Baseline (Day -27 to Day 1), Day 85 to Day 113]
To calculate the 'Change from Baseline', the HSV-2 genital shedding rate during the timeframe of Day 85 to Day 113 will be compared against the HSV-2 genital shedding rate during the timeframe of Day -27 to Day 1 (Baseline).
Change From Baseline (28 Days Prior to the First Study Injection) to 6 Months After the Second Study Injection in HSV-2 Genital Shedding Rate (Proportion of HSV-2 DNA Positive Anogenital Swabs) [Time Frame: Baseline (Day -27 to Day 1), Day 197 to Day 225]
To calculate the 'Change from Baseline', the HSV-2 genital shedding rate during the timeframe of Day 197 to Day 225 will be compared against the HSV-2 genital shedding rate during the timeframe of Day -27 to Day 1 (Baseline).
Alright friends, using “genital shedding rate” is what we call a surrogate outcome measure. Reminder that a surrogate outcome/endpoint is a measure that stands in for actual clinical outcomes. In this case, swabbing the genital area (with or without symptoms) and using PCR (not a test), in place of actual symptoms as an outcome.
Back to the bullshit…
Geometric Mean Titer (GMT) of mRNA-1608 Antigen-Specific Binding Antibodies (bAbs) at 1 and 6 Months After the Second Study Injection [Time Frame: Days 85 and 225]
Geometric Mean Fold Rise (GMFR) of mRNA-1608 Antigen-Specific bAbs From Baseline to 1 and 6 Months After the Second Study Injection [Time Frame: Baseline (Day 1), Days 85 and 225]
Number of Participants With Vaccine Seroresponse [Time Frame: Baseline (Day 1), Days 85 and 225]
Seroresponse is defined by an increase in HSV-2 bAb levels at Day 85 and Day 225 ≥4-fold if baseline level is above the lower level of quantitation (LLOQ) or ≥4 × LLOQ if baseline bAb level is <LLOQ prior to study injection.
AAAAANNNND we have another surrogate outcome measure folks, but this time it’s antibodies!! So after they inject a bunch of poison, TWICE, they are going to test and see if there’s an immune response by looking for magical chemical potions antibodies. Brilliant. GMT supposedly predicts potential protection, but doesn’t directly measure anything like actual disease prevention. It sounds very fancy and technical, doesn’t it. Geometric Mean Titer. They run neutralization assays, which I’ll talk about more in a moment, at multiple dilutions of a person’s blood serum. The highest dilution where antibodies are still “detectable” determines that person’s titer. Then they calculate the geometric mean titer (GMT) across everyone in the group
GMFR stands for Geometric Mean Fold Rise. This supposedly shows how much antibody levels increase after being injected with poison twice, compared to before the double jab poisoning.
How do they do it?
ELISA Plate
👇This is an ELISA plate*. It is commonly used in Signal Sorcery to “show” antibodies and determine things like Geometric Mean Titers (GMT) and Geometric Mean Fold Rise (GMFR).
*For the record, I do not know if this exact product is what they used in the clinical trial we are presently discussing.
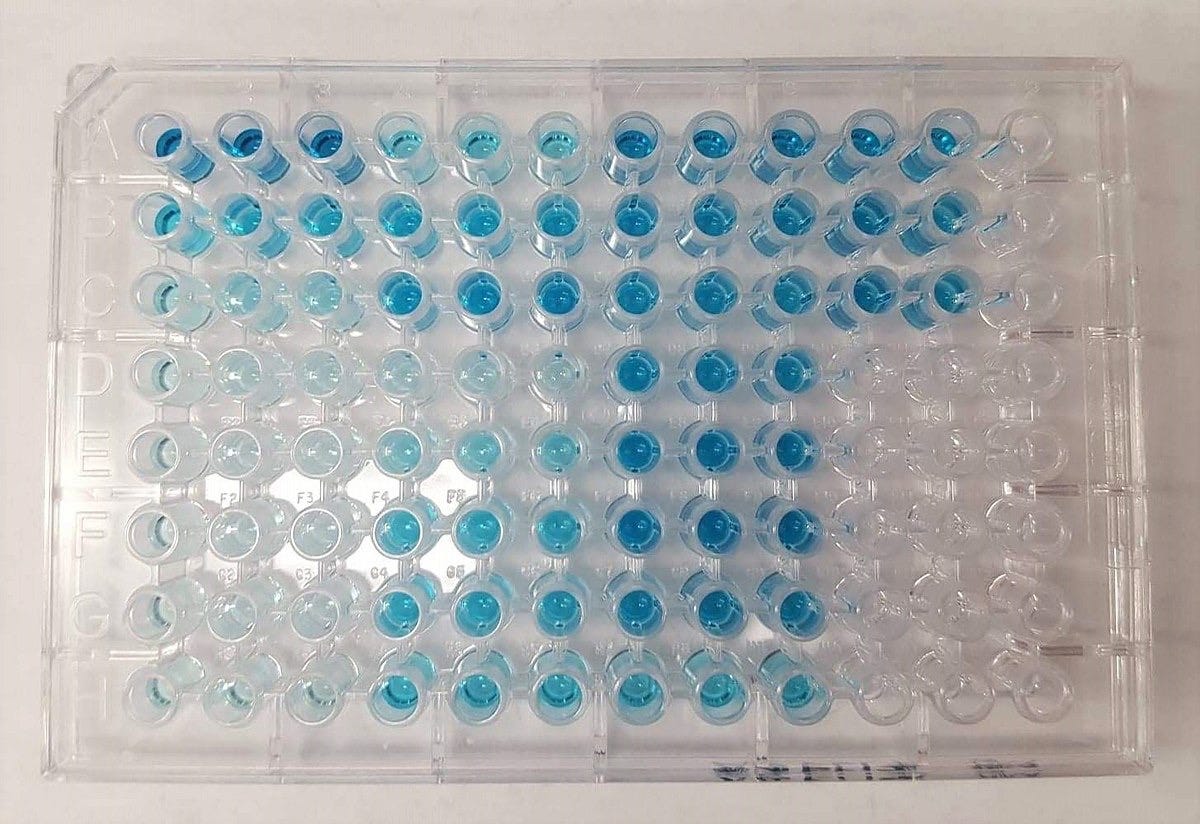
👆Just in case you are thinking there are just patient samples and antibodies up in those little test tubes, let me just clear that up for you.
Here is a list of what is commonly used in an ELISA assay plate:
1. Blocking Solution
This supposedly prevents “sticky” background noise by covering unused surfaces 🤣
Common blockers:
Bovine Serum Albumin (BSA)
Casein (milk protein)
Gelatin
Non-fat dry milk
Synthetic blocking buffers
2. Sample
Serum, plasma, cell culture supernatant, or other biological fluid containing the unknown antibodies or antigens.
3. Detection Antibody (secondary antibody)
Usually enzyme-linked (conjugated)
Common enzyme conjugates:
Horseradish Peroxidase (HRP)
Alkaline Phosphatase (AP)
4. Wash Buffer
(“removes” unbound stuff between steps 😂)
PBS + Tween-20 (PBST)
Tris-buffered saline + Tween (TBST)
5. Substrate / Chromogen
(reacts with the enzyme to make a visible color)
For HRP: TMB (3,3′,5,5′-tetramethylbenzidine) → turns blue/yellow
For AP: pNPP (p-nitrophenyl phosphate) → turns yellow
6. Stop Solution
Stops the reaction at a specific time so color doesn’t keep developing.
Sulfuric acid (H₂SO₄)
Hydrochloric acid (HCl)
Sodium hydroxide (NaOH)
Well that’s a lot of ingredients…to show the antibodies.
Now I can’t say for sure how they are measuring antibody response in this trial…but here’s how some patent holding scientists at Pfizer did it for their Herpes Zoster injection:
A highly stable lyophilized mRNA vaccine for Herpes Zoster provides potent cellular and humoral responses
Abstract
Herpes zoster (HZ) is a painful vesicular rash that occurs upon varicella-zoster virus (VZV) reactivation in older adults and immunocompromised individuals. Although there is currently an approved vaccine for the prevention of shingles, its administration is commonly associated with high reactogenicity. This highlights the need to develop new vaccine alternatives with long lasting immunity and improved tolerability upon administration. In the present study, 10 different vaccine candidate designs using two different codon optimizations targeting the VZV glycoprotein E (gE) were generated. A subset of mRNA constructs were formulated into lipid nanoparticles and assessed for their ability to induce specific cellular and humoral immune responses following vaccination in mice.
Vero cells (ATCC, CClL-81) were used to test drug substance (DS) or LNP-formulated material (DP). DP was directly delivered into cells by diluting the LNPs in Dulbecco’s phosphate-buffered saline (DPBS) without Calcium and Magnesium (Gibco). DS was delivered into cells using lipofectamine MessengerMax (Invitrogen, LMRNA015) and following manufacturer’s guidelines. After 16 h incubation period, transfection media was removed. Cells were then washed 3 times with PBS, fixed with 4% paraformaldehyde (PFA) (Invitrogen, 28908), and washed twice with 3% BSA (Millipore Sigma, 126626). Cells were stained with human monoclonal antibody against VZV gE (303-1A8) that was generated in house as previously described48. Antibody was diluted in a solution containing 0.1% saponin (Alfa Aesar) in 10% normal goat serum (Life Technologies, 50197Z). Antibody was incubated for 1 hour at 37 °C, followed by 3 washes with PBS. Alexa Fluor 488 secondary antibody (Invitrogen, A11013) was prepared at a 1:500 dilution along with a 1:140,000 dilution of HCS CellMask Orange Stain (Invitrogen, H32713) in the same solution previously used to incubate the primary antibody and incubated for 45 min at 37 °C. For nuclear cell staining, a 1:10,000 dilution of DAPI (Thermo Scientific, 62248) was incubated for 15 min at RT. After 3 washes with PBS, 96 well plates (Perkin Elmer, 6055508) were sealed and scanned with Opera Phenix Plus High Content Screening System (Perkin Elmer).
Sounds good, I’ll just go ahead and stop there. I’m just so impressed that they know that the perfect number of times to wash antibody after 10% goat serum is 3.
And a 1:140,000 dilution of HCS CellMask. Perfection!
I mean…1:140,001 would have obviously been overkill.
To summarize…
The Very Contagious Symptomatic-Asymptomatic Chucky Virus that robo-chops mRNA and loves to play hide and seek in nerves has never been isolated.
NEVER ISOLATED FROM EVERYTHING ELSE. Not once.
It supposedly infects almost everyone whether they know it or not. And the only real way to know is by using a “test”. This test cannot possibly be validated because you cannot clinically diagnose the Herp.
Despite Scoglio’s dismantling of the entire mRNA lipid nanoparticle platform as anything other than a toxic bomb, it is being used to develop new mRNA/LNP injections for the never isolated herpes “virus”.
The new mRNA-1608 Herp injections have already completed Phase 1 and Phase 2 clinical trials.
The mRNA-1608 trials have multiple problematic features including:
Meningococcal injection is used instead of an inert placebo.
Symptoms occurring during the 71 days after receiving the toxic injection are not counted.
Surrogate outcomes are used to determine efficacy.
Why do I continue to belabor this no-virus-has-ever-been-isolated thing?
Why do I want to look at the trials for an injection that prevents a purported virus that’s never been isolated? Especially when most people reading this have likely already decided they won’t be injecting anything like mRNA-1608 into their body?
Because it is following a blueprint of bullshit. It’s a pattern. That’s being repeated.
This process called isolation is truly unbelievable at first. At least it was for me.
But the more you look for it, the more you see it repeated, and the easier it gets boil it down to exactly what it is. Bullshit. And the more people that understand this and continue to talk about, the better.
Now I would like to explain why, in my opinion, the sex viruses are particularly important beyond the ways they’ve been used to force regulatory bypass and accelerated approval.
Sex Viruses
The diseases I’ve discussed recently are supposedly contracted by engaging in behavior that is fundamentally human. Acts of physical touch; intimacy, lovemaking, and procreation. Behavior almost every human on the planet will engage in.
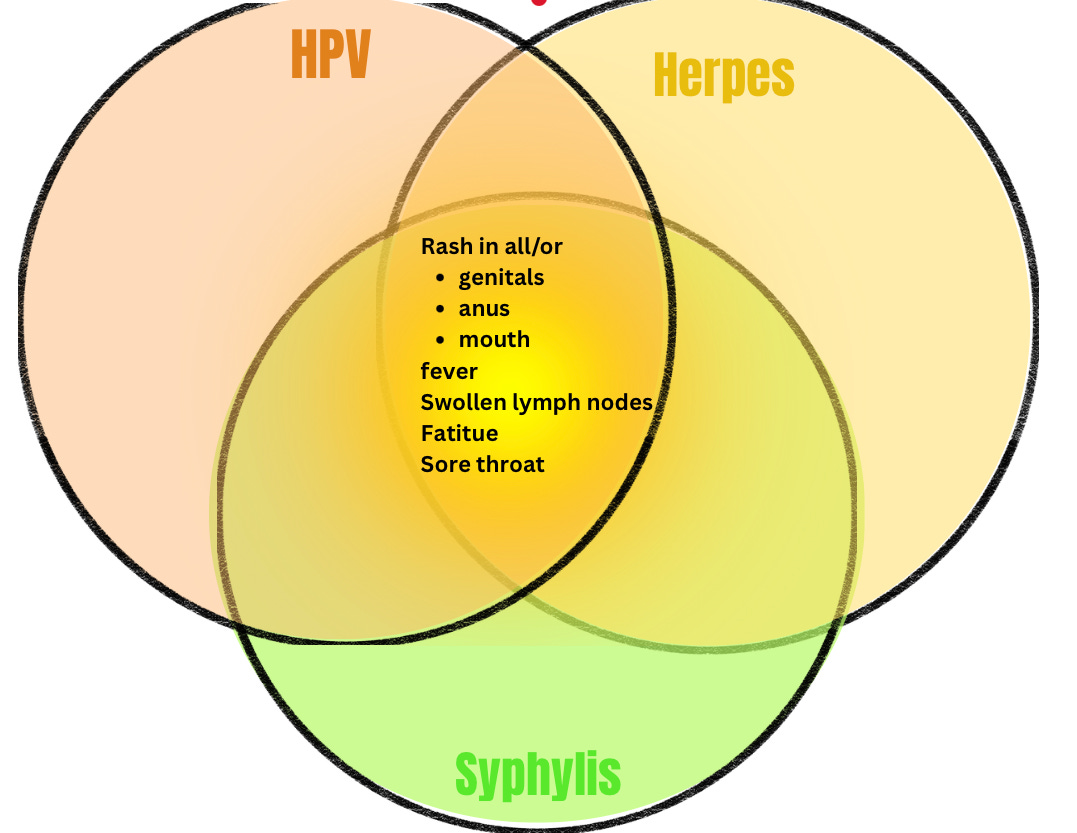
But the diseases aren’t distinct.
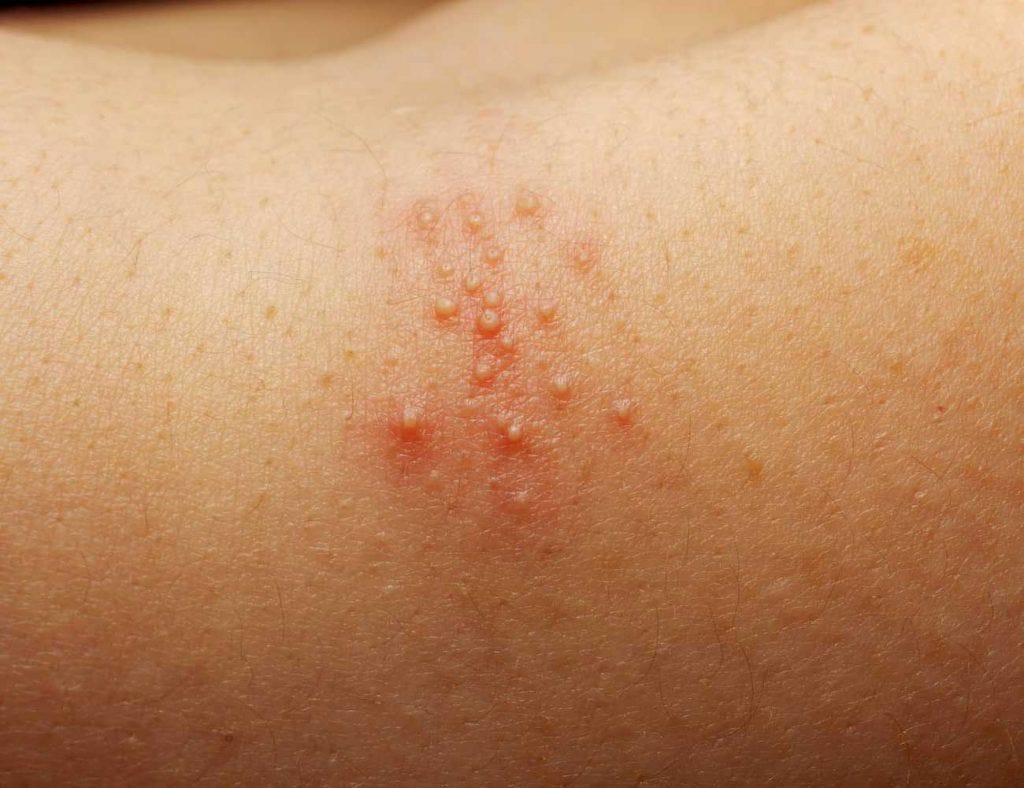
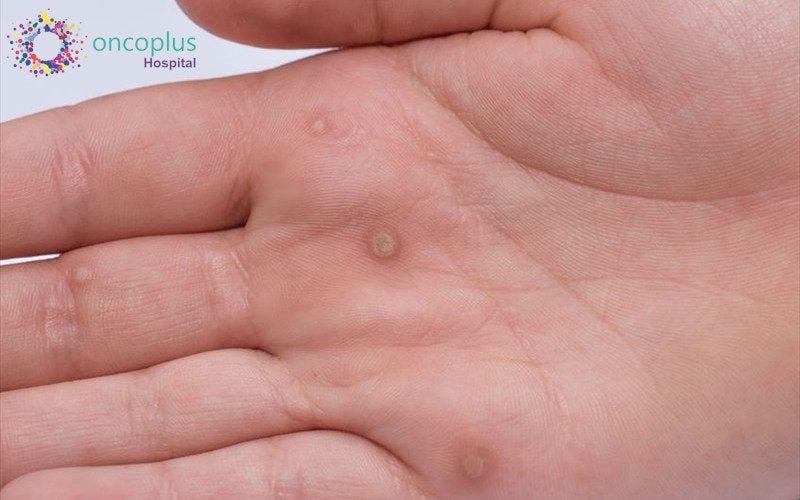
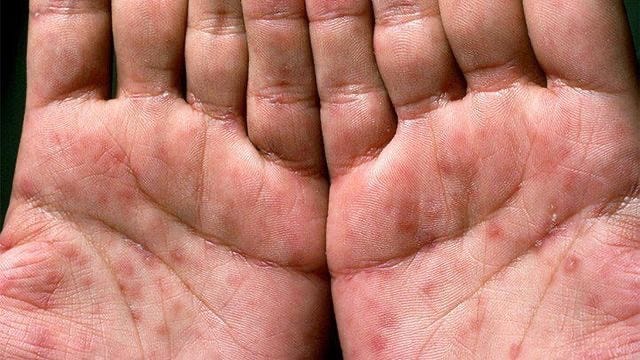
They need a test.

The test can’t be validated though. Because the supposed virus has never been isolated and you simply cannot know for sure that someone has it. Because they all have overlapping symptoms.
Isolation of “the virus” always involves adding some sort of (usually) not human cells, fetal calf or other animal serum, maybe some modified eagle’s medium, and a bunch of other chemicals…which is NOT isolation. No matter how many different ways you mix them or how many Gs you use to spin them. No matter what color stain you use. Or how many pictures you take of dead tissue.
Increasingly toxic injections are being deemed necessary, based upon this faulty and fraudulent foundation. They are developed using equally inadequate evidence of safety and efficacy, which continues to move ever further from anything tangible. They are deployed under the guise of personal and public health.
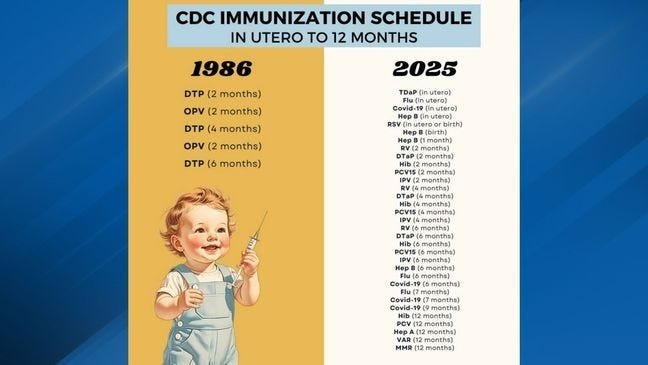
For children. In anticipation of their participation in behavior that is largely unavoidable, and fundamentally human. The behavior which populates the planet and perpetuates our species is being weaponized in many ways.
And this is one of them.
From a psychological operation perspective, the sex viruses are going to be an incredible motivator for my generation (X) to inject their children. We were born in the midst of a raging sexual revolution that continues to accelerate.
We were raised by boomers who were brought up by the trauma of post WW2 parents. Boomers also received a heavy dose of imposed sexualization. Our parents ate a wholesome and steady diet of traditional family values for breakfast, lunch, and dinner until they got naked and high…and made all the love and bad decisions.
Gen X came up on the heels of a cultural shift that had been soaked in propaganda and drugs, and perpetuated by the unseen hand of the CIA and its many programs, which I discussed here.
We got a lot of messaging about sex at an early age, largely by the public education indoctrination system and somewhat by our damaged parents.

Also by the TV and radio. Followed by the internet.
All of it, wildly conflicting.








And now we have kids. That are being exposed to a digital world that has created an entirely new situation that they will need to navigate.

Rest assured that all of these factors are well understood and will be leveraged by the murderers of the world. And by leveraged I mean exploited to the fullest extent.
HPV injections are already being peddled as a way to prevent our children from suffering the terrible cancer fate…a fate by which many of us have watched our parents suffer.
These new injections will be sold to us as a way to protect our children from the experience of a “very contagious” genital rash. The imprint of mixed messages, riddled with fear and stigma, that we carry with us from the sex education of our formidable years is an undercurrent that shouldn’t disregarded. Many will be compelled to give their daughters and sons these injections in an effort to prevent something we have been told to fear for most of our lives. The propaganda living in the subconscious will make this a very easy decision for a lot of parents. Just look at how easily HPV injections slid into the childhood vaccine schedule.
Fertility…add another shot
At this point no one can possibly know how these mRNA-1608 injections will affect fertility (😉). But we can sure as shit take an educated guess by looking at what has happened to fertility since the covid jabs. And we can look to birthrates trends since we started sticking children like pin cushions.
How it’s going…

The fertility rate in the U.S. dropped to an all-time low in 2024 with fewer than 1.6 children being born per woman, federal data released Thursday shows.
The U.S. was once among only a few developed countries with a rate that ensured each generation had enough children to replace itself — about 2.1 kids per woman. But it has been sliding in America for close to two decades as more women are waiting longer to have children or never taking that step at all.
And 2025 Is Even Worse
What To Know:
The United States has a fertility rate (births per woman) of 1.58 so far in 2025—down from 1.59 last year, 1.60 in 2023, 1.64 in 2020 and 1.84 in 2015.

It’s not complicated.

Correlation doesn’t equal causation blah blah blah…
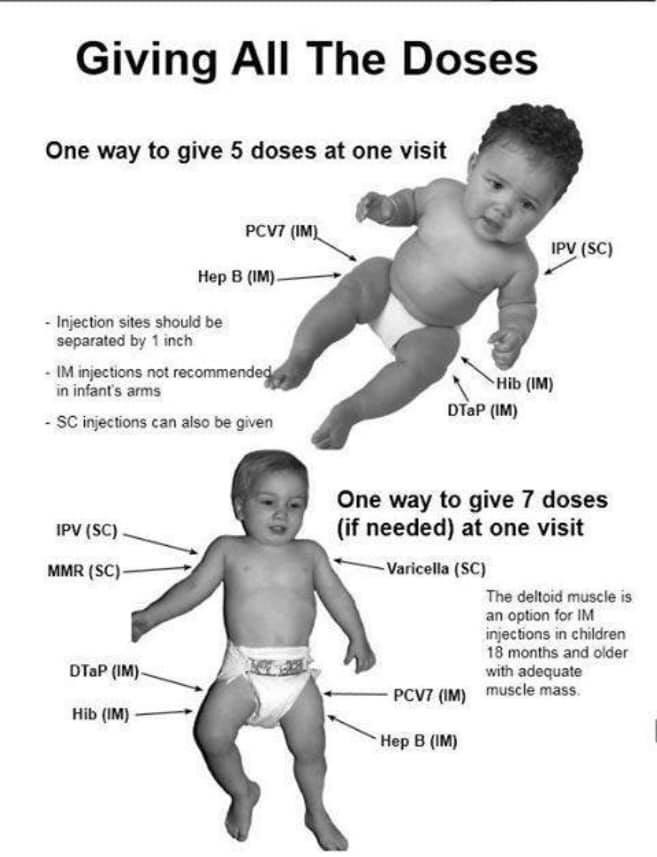
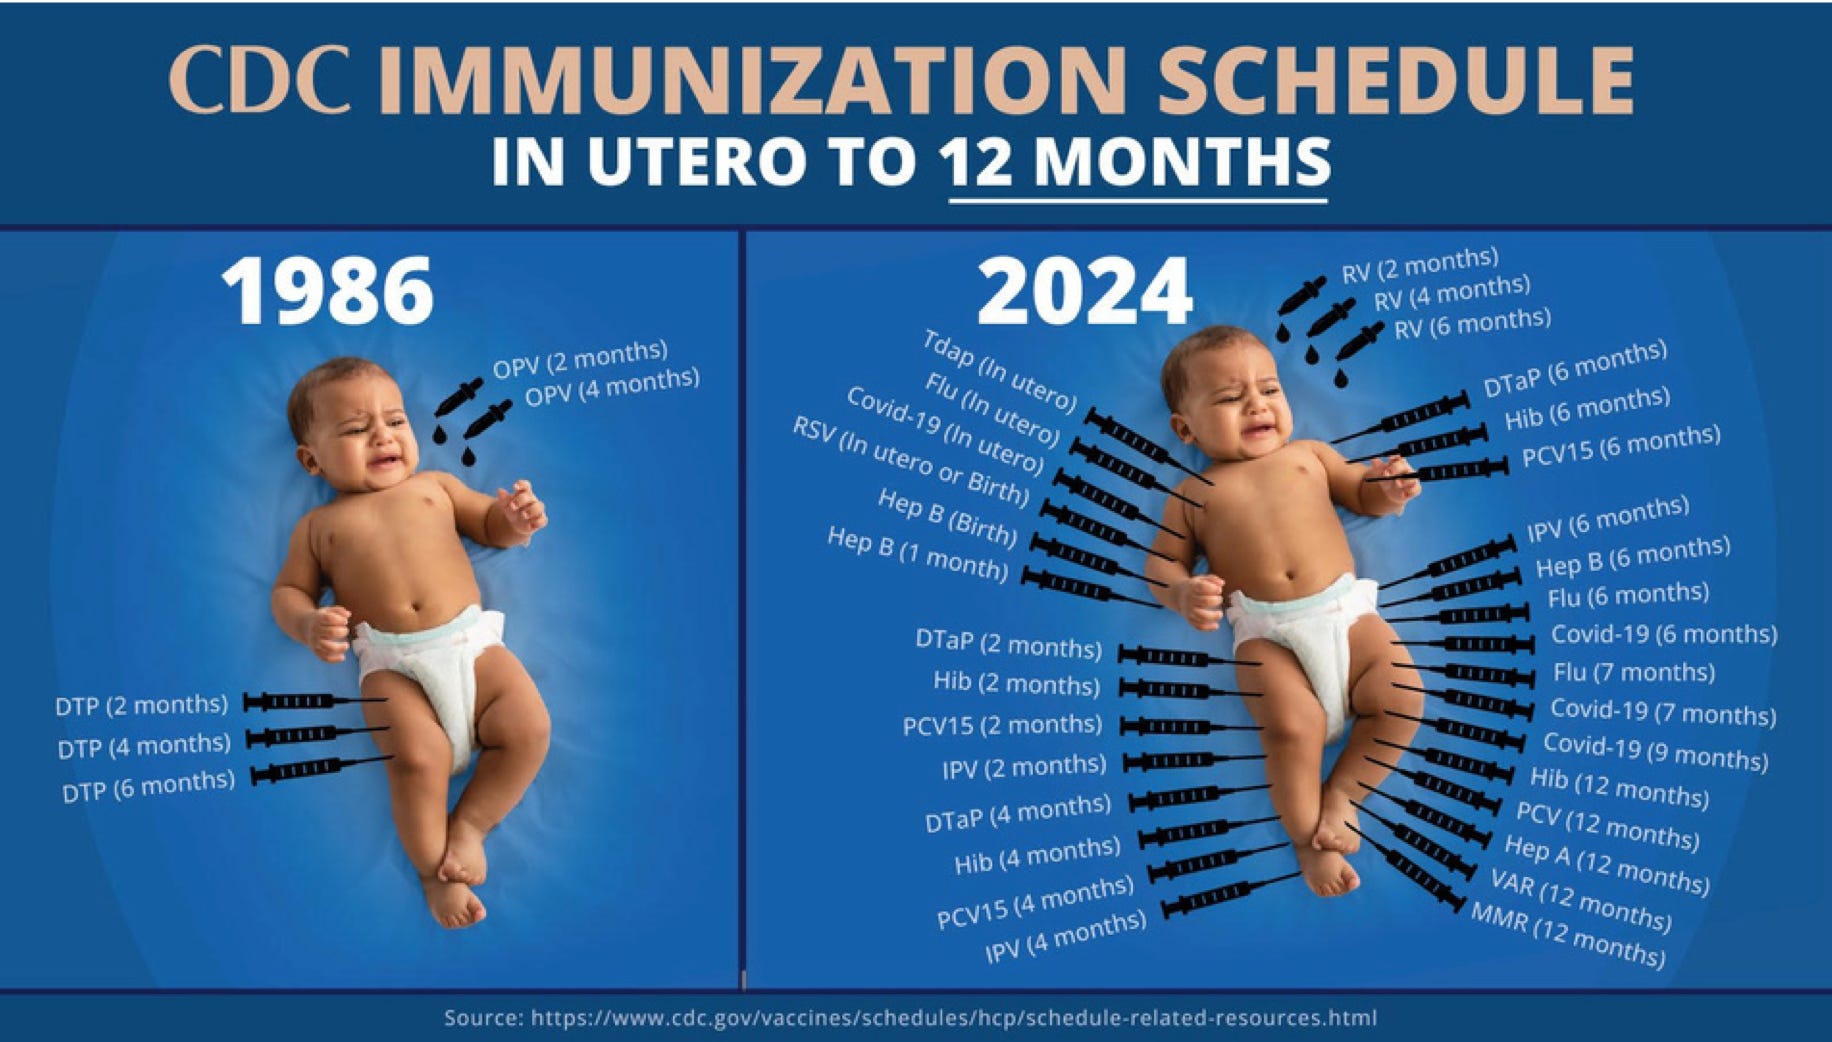
I’m not going to say that it’s vaccines alone causing the precipitous fall in birth rates…

Because we all know it’s the red dye.

Also, last I checked nobody’s ovaries or testes are deficient in lipid nanoparticles loaded with toxic sludge. And ovaries and testes are kind of a big deal when it comes to making babies.
So I will also say that there is nothing about the Japanese Biodistribution Study that indicates that injecting more mRNA/LNP bullshit will help anyone have more babies.



Here’s the thing guys. The murderers of the world told us what they were going to do. And now they’re doing it. It’s up to us to call the bullshit out when we see it. Nobody is coming to save us.
The emperor is wearing monkey kidney cells and fetal calf serum and hoping nobody notices that he’s actually the pied piper.


“One of the most serious challenges to human destiny in the last third of this century will be the growth of the population.”

Bill Gates has a warning about population growth









Excellent work Sarah! Thank you for all that you do. I am with you 100%. Keep asking the basic questions and keep exposing the layers upon layers of fraud and deception. While I was in the system, I blindly believed what I was taught and was rewarded for following along. Now that I am a retired physician (retired in 2018 - just in time!), I can see it all so clearly. Keep up the great analysis! I always enjoy your articles.
Epic, Sarah!
Currently I’m at loggerheads with a new Vet who’s insistent on vaccinating my puppy for parvovirus.
IT’S EVERYWHERE! IT PERSISTS IN THE SOIL FOR A YEAR!!
Ultimately, I told her to find the original paper that isolated parvovirus and we can do it.
Crickets…